
Introduction
Sustainable medical education financing has emerged as a major policy concern for health systems worldwide. Rising educational costs, demographic transitions, rapid technological advancements, and increasing demands for high-quality and accountable health professionals have substantially pressured traditional public financing models (1-4). In low- and middle-income countries (LMICs), these pressures are intensified by fiscal constraints, economic volatility, and competing budgetary priorities, threatening the long-term sustainability of medical education and, by extension, health workforce development (5-8).
Sustainable financing refers to a financing system's capacity to generate and maintain adequate, predictable, fair, and resilient resources over time while adapting to changing economic and policy conditions (9, 10). In medical education, financing sustainability extends beyond fund availability to include long-term financial stability, diversification of funding sources, protection against fiscal shocks, and the ability to support educational quality and health workforce development. For this study, sustainable financing is operationally examined through stockholder's perceptions of funding adequacy, stability, diversification, resilience to economic pressures, and the long-term capacity of financing arrangements to support medical education.
Despite the growing importance of sustainable financing for medical education, existing scholarship has focused on funding mechanisms, expenditure patterns, cost-containment strategies, and resource allocation models within higher and medical education systems (2, 10). While these studies have generated valuable insights into the structure and performance of financing arrangements, less attention has been devoted to understanding the policy processes through which financing challenges are recognized, framed, and elevated on governmental agendas. In particular, applying policy process theories—such as Kingdon's Multiple Streams Framework—to medical education financing remains limited, and few studies have explored how contextual factors, political dynamics, policy actors, and competing institutional interests shape financing reform agendas (11-13). Important questions remain regarding how sustainable financing emerges as a policy priority, especially in low- and middle-income countries experiencing fiscal constraints, economic volatility, and competing health sector demands.
This study analyzes the agenda-setting process for financing sustainability in medical education in Iran — an upper-middle-income country experiencing prolonged international sanctions, high inflation, and significant fiscal pressures on public services. Specifically, the study aims to: 1) identify the key structural, economic, political, and technological factors influencing financing of medical education; 2) examine how these factors interact within the policy process using an integrated theoretical approach; and 3) explain the conditions under which sustainable financing reforms emerge on the policy agenda. Findings should generate transferable insights for other health systems facing similar structural challenges.
Methods
This study was conducted in five exploratory sequential phases: 1) a scoping review of the literature, 2) semi-structured interviews, 3) qualitative content analysis and theme development, 4) a four-round Delphi study, and 5) integration of the findings using Kingdon's Multiple Streams Framework and the Policy Triangle to develop a comprehensive agenda-setting model (Figure 1).
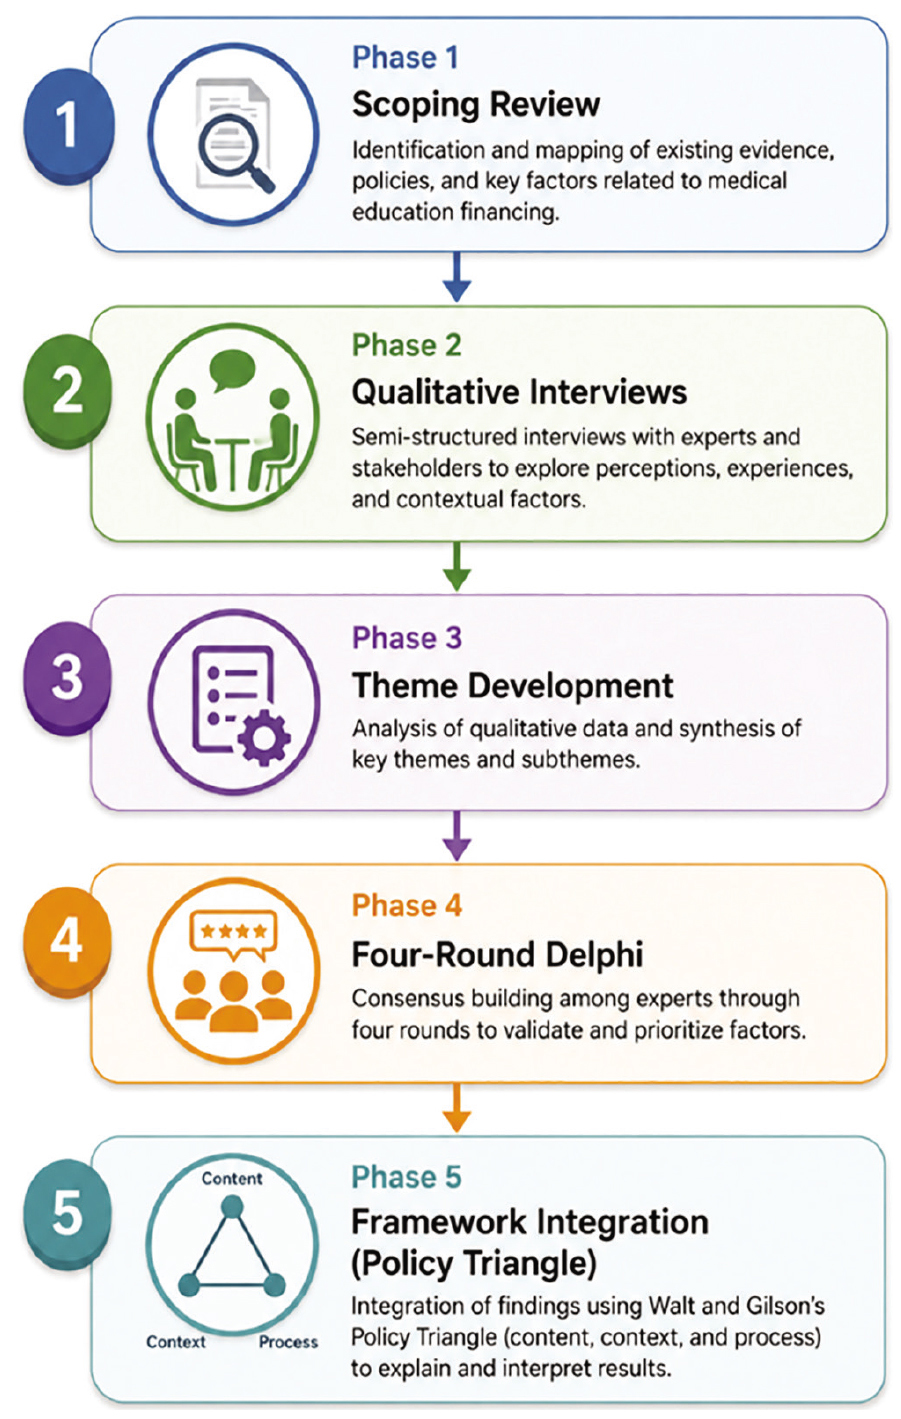
Figure 1.Research process steps
Ethical Approval
All procedures were performed in accordance with the ethical standards of the Declaration of Helsinki. Written informed consent was obtained from all participants before each phase. Participation was voluntary, and participants could withdraw at any time without any negative consequences. Ethical approval for this study was obtained from the Research Ethics Committees of the National Agency for Strategic Research in Medical Education - Iran (Code: IR.NASRME.REC.1403.129).
1) Scoping Review of the Literature
To map and synthesize the existing evidence on financing sustainability in medical education; identify key concepts, knowledge gaps, and policy-relevant factors; and inform the subsequent qualitative interviews and Delphi process, we conducted a scoping review. The review followed the Joanna Briggs Institute (JBI) methodology for scoping reviews and was reported in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses Extension for Scoping Reviews (PRISMA-ScR) guidelines.
Eligibility Criteria
Studies were considered eligible if they focused on medical or medical sciences education at either undergraduate or postgraduate level. The core concepts of interest included financing, funding, costs, economic models, sustainability, resource mobilization, and payment mechanisms. No restrictions were applied based on geographical context; thus, studies from any country were included. Eligible sources encompassed peer-reviewed journal articles, systematic or scoping reviews, policy documents, reports, and relevant grey literature. Only publications released between January 2010 and December 2024 and written in English or Persian were considered.
Information Sources and Search Strategy
A comprehensive search was conducted in the following electronic databases from inception to December 31, 2024: PubMed/MEDLINE, Scopus, Web of Science, ProQuest, and Google Scholar. No limits were applied regarding the publication country. The search strategies were developed using a combination of controlled vocabulary and free-text terms.
Study Selection and Quality Assessment
All identified records were screened for duplicates and then removed. Two reviewers independently screened the titles and abstracts, after which the full texts of potentially relevant studies were reviewed; any discrepancies were resolved through discussion or by consulting a third reviewer. A standardized data extraction form was developed and pilot-tested to chart data including author, year, country, study aim, methodology, population or sample, key financing themes, main findings, and implications. Data were independently extracted by two reviewers and subsequently verified for accuracy. Although quality assessment is not mandatory in scoping reviews, the methodological quality of the included primary studies was appraised using the Mixed Methods Appraisal Tool (MMAT, 2018) to enhance the rigor and interpretability of the findings. Each study was rated as high, moderate, or low quality; studies rated as low quality were not excluded, but their limitations were considered when interpreting the results.
The search yielded 145 records. After removing 32 duplicates, 113 records were screened by title and abstract; of them, 40 were excluded for being irrelevant to the topic, having the wrong population or context, or falling outside the specified time frame. The remaining 29 records were retained for further content analysis.
2) Qualitative Interview
Participant Selection
Purposive maximum variation sampling was used to recruit 15 key informants from four stakeholder groups: health system managers (n=3), medical faculty members (n=7), policymakers/former or current members of parliament (n=2), and senior residents/PhD students (n=3). Participants had at least 10 years of relevant professional experience. Participants were purposively selected based on their expertise and involvement in medical education financing, health policy, university governance, and related decision-making processes at the national level rather than geographical representation. Participant characteristics are summarized in Table 1.
| Variable | Category | Health System Managers | Faculty Members | Policymakers | Residents & PhD Students | Total |
|---|---|---|---|---|---|---|
| Age (years) | 40–50 | 1 | 2 | 0 | 3 | 6 |
| 50–60 | 2 | 5 | 2 | 0 | 9 | |
| Gender | Male | 3 | 4 | 2 | 2 | 11 |
| Female | 0 | 3 | 0 | 1 | 4 | |
| Work Experience (years) | 10–20 | 0 | 2 | 0 | 3 | 5 |
| 20–30 | 3 | 5 | 2 | 0 | 10 | |
| Total | - | 3 | 7 | 2 | 3 | 15 |
Data Collection
Semi-structured in-depth interviews were conducted in Persian, either face-to-face or via secure video conferencing (Zoom), based on participant preference. Interviews lasted between 45 and 75 minutes (mean: 58 minutes). An interview guide with open-ended questions and probes was used. All interviews were audio-recorded with permission and transcribed verbatim. Interviews continued until theoretical saturation was achieved, defined as the point at which no substantially new concepts, themes, or insights emerged from successive interviews.
Semi-structured interviews were conducted using a pre-developed interview guide.
Data Analysis
Transcripts were analyzed using framework analysis following Ritchie and Spencer's five-stage method. The interview data were analyzed using conventional content analysis. The process included familiarization with transcripts, open coding, comparison of codes across transcripts, development of categories, generation of themes, and iterative refinement. All steps were performed by multiple researchers to ensure consistency and rigor. MAXQDA 2022 software was used to facilitate data management and analysis. A combination of a priori codes (derived from the theoretical frameworks) and inductive codes was applied.
Use of Artificial Intelligence
ChatGPT-4o was used as a supplementary analytical aid during the qualitative analysis phase. Its use was restricted to three tasks: 1) generating concise summaries of interview transcripts, 2) suggesting preliminary codes based on transcript excerpts, and 3) identifying potential inconsistencies in coding across transcripts. AI was not used to make analytical decisions, generate themes, or draw conclusions. Only de-identified transcript segments were entered into the system after removal of all personal and organizational identifiers. The research team used structured prompts such as: "Summarize the main ideas expressed in this interview excerpt," "Suggest preliminary qualitative codes for this text," and "Identify similarities and differences between these coded excerpts." In some instances, iterative prompting was employed to refine the summaries or clarify the coding suggestions.
All AI-generated outputs were independently reviewed by at least two members of the research team. Suggestions were accepted only when they were consistent with the original transcript content and aligned with the study analytical framework. Suggestions that lacked contextual accuracy, introduced new interpretations, or conflicted with researcher judgment were modified or rejected. The final coding structure, thematic interpretation, and all analytical decisions were developed and validated manually by the researchers using MAXQDA 2022.
Trustworthiness
Trustworthiness was enhanced through multiple strategies. Peer debriefing was conducted by an independent qualitative researcher who was not involved in data collection. An audit trail was maintained documenting coding decisions, theme development processes, analytical memos, and iterative revisions to ensure dependability and confirmability of the analysis. Coding outputs and thematic classifications were reviewed independently by members of the research team. Differences in coding and categorization were discussed and resolved through consensus. Consistent with qualitative interpretive methodology, emphasis was placed on analytical consensus and transparency rather than statistical inter-coder reliability measures.
3) Qualitative Content Analysis and Theme Development
The initial pool of statements was generated through iterative coding of qualitative interview transcripts and findings from the literature review. Statements were subsequently reviewed for duplication, conceptual overlap, clarity, and relevance to the study objectives. Two members of the research team independently reviewed the coding structure and thematic categorization, and discrepancies were resolved through discussion and consensus. Similar statements were merged, redundant items were removed, and the remaining statements were grouped into broader thematic domains using constant comparative analysis. Theme development was iterative, with categories being refined throughout the analysis process to ensure conceptual coherence and alignment with the study objectives.
4) Delphi Process
The same 15 experts who participated in the interviews constituted the Delphi panel. A four-round modified electronic Delphi technique was conducted from March to June 2024. Anonymity was maintained throughout all rounds, and the response rate was 100% in every round.
- Round 1: Open-ended questions for factor elicitation.
- Round 2: Rating of consolidated items using a 5-point Likert scale (1=Not important at all to 5=Extremely important).
- Rounds 3 and 4: Participants received controlled feedback (group median and interquartile range) along with their previous scores and were asked to re-rate the items.
Consensus was predefined as ≥70% of panelists rating an item as 4 ("Important") or 5 ("Extremely important"). In addition, overall agreement among panelists was monitored across Delphi rounds using Kendall's coefficient of concordance (W). Improvement in inter-rater agreement was assessed through progressive increases in Kendall's W, reflecting convergence of expert opinions over time. The Delphi process continued until ratings demonstrated acceptable stability and no substantial changes in group responses were observed between successive rounds. As the objective was to facilitate consensus development rather than test statistical hypotheses, formal significance testing was not performed.
5) Analytical Framework and Data Integration
Data from all three sources were interpreted using Walt and Gilson's Policy Triangle and Kingdon's Multiple Streams Framework. Integration was performed at the interpretation phase through joint displays and narrative synthesis to identify convergence, complementarity, and dissonance between the data sources.
The two theoretical frameworks were applied sequentially and complementarily. Walt and Gilson's Policy Triangle served as the primary analytical framework for organizing and categorizing the findings according to four dimensions: context, actors, content, and process. These dimensions informed the development of the coding framework and guided the initial analysis of data from the literature review, interviews, and Delphi process.
Following this stage, Kingdon's Multiple Streams Framework was used as an interpretive framework to explain agenda-setting dynamics. Factors identified through the Policy Triangle analysis were examined in relation to the problem, policy, and political streams, and their potential convergence in creating a policy window for reform. The two frameworks were, therefore, not merged at the construct level; rather, they were used in a complementary manner, with the Policy Triangle providing a structural perspective and the Multiple Streams Framework providing a process-oriented explanation of policy emergence and agenda-setting.
Integration and Triangulation of the Findings
Data integration followed a sequential triangulation approach. The literature review identified preliminary factors, policy issues, and financing strategies relevant to medical education. Qualitative interviews were then used to explore these themes in greater depth and to capture context-specific perspectives. Findings from both phases informed the Delphi questionnaire, through which experts validated, refined, and prioritized the identified factors. Areas of convergence across sources were interpreted as strengthened evidence, while divergent findings were retained and discussed to reflect the complexity of policy processes and stakeholder perspectives.
Results
Structural Drivers from International Evidence
The synthesis of international literature revealed that financing of medical education was influenced by multiple interrelated structural drivers that mostly lie beyond the control of individual academic institutions. These drivers were categorized into seven major domains: globalization, demographic change, economic conditions, social dynamics, political factors, ideological orientations, and the share of higher education within GDP or total health expenditure. A detailed summary of these domains and supporting references is presented in Table 2.
| Domain | Key Factors/Sub-dimensions | Main References |
|---|---|---|
| Globalization | International accreditation, global rankings, competition among medical schools | (1, 14-20) |
| Demographic change | Declining youth population, population ageing, changing student socioeconomic profile | (1, 5-7) |
| Economic conditions | Inflation, economic recession, declining public investment, fiscal austerity | (1-2, 7, 9, 14-18, 20) |
| Social dynamics | Equity expectations, social accountability, public pressure for access | (1-3, 5, 7, 9, 17-18) |
| Political factors | Political cycles, short-term budgeting, prioritization policies | (1-2, 6, 10, 12, 17-19) |
| Ideological orientations | Commitment to free education, role of state in higher education, social justice | (6, 18) |
| Share of education in GDP/health expenditure | Low budget allocation to education and medical training | (2-3, 5-7, 9, 12) |
Contextual Factors Identified in Qualitative Interviews
Analysis of the 15 semi-structured interviews yielded 79 initial statements, which were consolidated into 71 distinct statements and subsequently organized into eight thematic domains through an iterative process of thematic refinement and researcher consensus. Technological factors emerged as an additional domain not prominently identified in the initial literature review.
Participants strongly emphasized macroeconomic pressures -particularly high inflation, international sanctions, currency instability, and declining public investment in higher education- as the most critical challenges to sustainable medical education financing. These factors were described as not only limiting institutional budgets but also exacerbating social, regional, and gender-based inequities in access to medical education.
Political and governance issues were also frequently mentioned, including unplanned expansion of medical education capacity without adequate funding, political prioritization of specific groups (quota systems), delayed reimbursements from public insurance organizations, and short-term budgetary decision-making. Technological advancements (e.g., e-learning platforms, artificial intelligence, and simulation-based training) were viewed as a double-edged sword: offering potential efficiency gains while demanding significant upfront capital investment. Representative quotations from participants illustrating these themes are presented in Table 3.
| Domain | Mean Score (1–5) | SD | Agreement (%) | Consensus Level |
|---|---|---|---|---|
| Economic conditions | 4.89 | 0.64 | 97.8 | Strong |
| Low share of education in GDP / health expenditure | 4.89 | 0.59 | 97.8 | Strong |
| Demographic change | 4.87 | 0.47 | 97.4 | Strong |
| Technological factors | 4.87 | 0.41 | 97.5 | Strong |
| Political factors | 4.82 | 0.55 | 96.4 | Strong |
| Social dynamics | 4.60 | 0.35 | 92.0 | Good |
| Ideological orientations | 4.60 | 0.71 | 92.0 | Good |
| Globalization | 4.33 | 0.62 | 86.6 | Moderate |
| Overall Average | 4.73 | 0.54 | 94.67 | Strong |
| Agreement (%)=Percentage of experts rating the domain as "Important" or "Extremely important" (score 4 or 5). Consensus was predefined as ≥70% agreement. | ||||
Expert Consensus on Priority Drivers: Delphi Results
In the four-round Delphi process, 62 out of 71 consolidated statements (87.3%) met the predefined consensus criteria and were retained as key drivers of sustainable medical education financing. As shown in Table 3, the highest mean importance scores and levels of expert agreement were observed for economic conditions and low share of education in GDP and health expenditure (mean=4.89/5, agreement=97.8%). Demographic change, technological factors, and political factors also received very strong consensus (mean scores>4.80, agreement>96%). Social and ideological domains, although still highly rated, received comparatively lower scores and were interpreted as reinforcing rather than primary drivers.
Findings Organized According to the Policy Triangle Framework
Before applying Kingdon's Multiple Streams Framework, the findings from the literature review, interviews, and Delphi process were organized according to Walt and Gilson's Policy Triangle. This analysis revealed four interrelated dimensions shaping the financing of medical education.
Context factors included inflation, international sanctions, demographic transitions, technological developments, globalization pressures, and the low share of medical education within GDP and health expenditure. These factors collectively created a challenging environment for sustainable financing.
Actors included policymakers, health system managers, university leaders, faculty members, students, and other stakeholders involved in financing and governance decisions. Participants highlighted the differences in priorities and influence across these actor groups, particularly regarding funding allocation and reform implementation.
Content referred to the financing alternatives and policy options discussed by stakeholders, including continued public funding, cost-sharing mechanisms, performance-based financing, private-sector engagement, and hybrid financing models.
Process factors encompassed agenda-setting activities, stakeholder negotiations, policy discussions, and attempts to align financing reforms with broader health and education priorities. These processes were influenced by both institutional constraints and political considerations. The Policy Triangle analysis provided a structural understanding of the financing landscape, which subsequently informed interpretation of agenda-setting dynamics through Kingdon's Multiple Streams Framework.
The identified findings emerged through a sequential integration of evidence sources. Several contextual challenges, including inflation, sanctions, and demographic pressures, were initially identified in the literature review and subsequently confirmed by interview participants and Delphi panelists. Policy options such as financing diversification, performance-based funding, and public–private partnerships emerged primarily from interviews and were later refined and prioritized through the Delphi process. Areas of divergence across sources were not excluded; instead, they were examined as reflecting differences in stakeholder perspectives and policy priorities, thereby contributing to a richer understanding of agenda-setting dynamics.
Agenda-Setting Dynamics: An Integrated Multiple Streams Analysis
Building on the Policy Triangle analysis, we subsequently interpreted the identified contextual factors, actors, policy options, and policy processes using Kingdon's Multiple Streams Framework to explain how sustainable financing emerged as a policy issue and how opportunities for reform were created. Integration of data from the literature review, interviews, and Delphi process enabled reconstruction of the agenda-setting process using Kingdon's Multiple Streams Framework.
- Problem Stream: Macroeconomic pressures, particularly inflation, sanctions, and insufficient public funding, overwhelmingly dominated this stream. These were compounded by demographic shifts, technological demands, and rising social expectations for equitable access.
- Political Stream: This stream was shaped by ongoing tensions between strong political commitments to free education and expanded access on one hand, and severe fiscal constraints, ideological positions, and external political pressures (including sanctions) on the other.
- Policy Stream: A variety of financing alternatives were circulating within policy networks, including full public funding, cost-sharing, privatization, performance-based funding, and hybrid public-private models. However, experts noted that these options remain largely fragmented and have not been sufficiently institutionalized.
Convergence of Streams and Policy Window
The findings indicate that the three streams have increasingly converged, creating conditions conducive to the opening of a policy window for sustainable financing reform. Nevertheless, participants consistently highlighted that realization of this window heavily depended on the presence of effective policy entrepreneurs who could couple the streams and translate ideas into actionable policy proposals. The reconstructed agenda-setting model for sustainable medical education financing is illustrated in Figure 2.
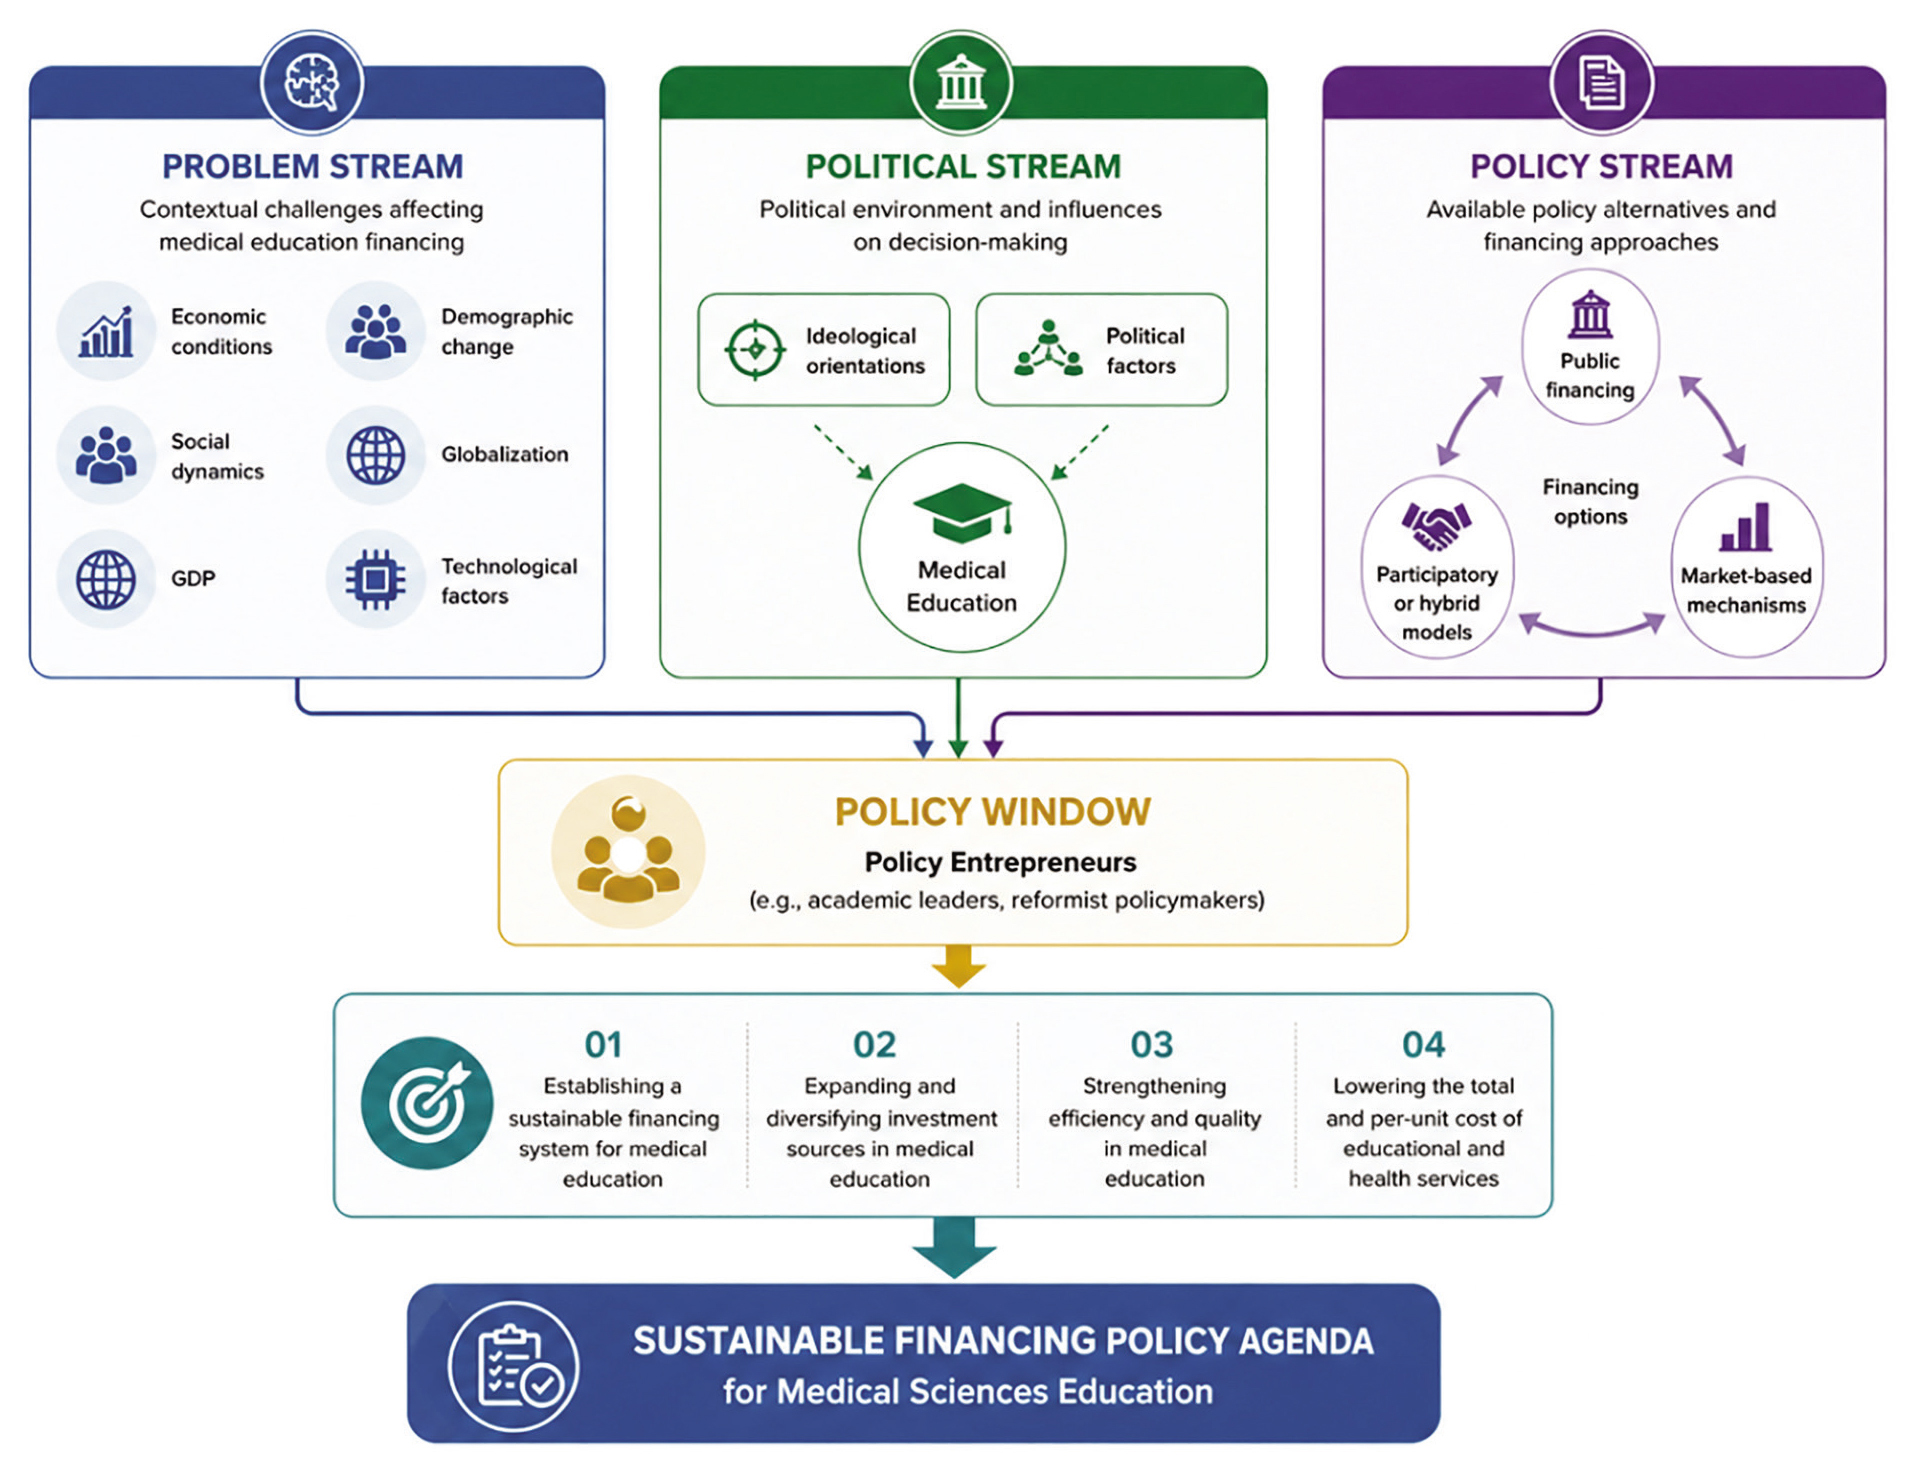
Figure 2.Sustainable financing of medical education model.
Discussion
In this study, we analyzed the agenda-setting process for sustainable financing of medical education by integrating Kingdon's Multiple Streams Framework with Walt and Gilson's Policy Triangle. The findings demonstrate that challenges in financing medical education are not merely technical or budgetary issues, but deeply political and institutional phenomena that emerge from the complex interaction of structural pressures, governance arrangements, and actor dynamics. This interpretation is consistent with the broader health policy literature, which emphasizes that financial decision-making in education and health is embedded within larger political and institutional processes (11-12).
Problem Stream: Structural Pressures and Problem Recognition
The findings indicate that the problem stream has been primarily shaped by severe macroeconomic pressures, including chronic inflation, government fiscal constraints, international sanctions, and the sustained rise in the costs of medical education. These factors have transformed long-standing resource limitations into an urgent policy problem through visible indicators such as declining educational budgets and widening gaps between available resources and actual expenditures (1-2, 7, 9, 14, 18-24). Reinforcing this problem stream are several structural factors, including demographic changes, globalization of medical education standards and competition, rising social expectations for quality and equity, rapid technological advancements, and the persistently low share of medical education within gross domestic product and total health expenditure (1-9, 12, 17, 18-23, 25). Consistent with Kingdon's Multiple Streams Framework, these elements function as both indicators and chronic conditions that have collectively heightened policymakers' perception of financial unsustainability.
Political Stream: Governance, Ideology, and Institutional Constraints
The political stream is characterized by ongoing tensions between strong ideological commitments to free education and expanded access, short-term budgetary priorities, political cycles, centralized fiscal governance, and external constraints such as sanctions. These dynamics significantly limit the advancement of structural financing reforms (1-2, 6, 10, 12, 17-18, 26). The study findings align with international evidence showing that political alignment and favorable ideological conditions are essential prerequisites for financial reforms to gain agenda status. In the absence of such alignment, even well-recognized problems and available solutions rarely translate into concrete policy action.
Policy Stream: Availability of Solutions and Weak Policy Coherence
A range of potential financing options circulates within policy networks, including diversification of funding sources, performance-based mechanisms, and greater participation of the non-state sector (2, 3, 5–7, 10, 18, 27-29). However, these alternatives largely lack sufficient policy coherence and institutional alignment. As Kingdon's "policy primeval soup" concept suggests, only those alternatives that are technically feasible, normatively acceptable, and institutionally compatible tend to survive and mature (11). The current fragmentation in the policy stream has limited the maturation and institutionalization of viable financing models.
Policy Window and the Role of Policy Entrepreneurs
A central finding of this study is the convergence of the problem, political, and policy streams, which collectively created a policy window for advancing sustainable financing reforms in medical education. Participants consistently described increasing fiscal pressures, growing recognition of financing challenges, and the availability of feasible policy alternatives as the factors that aligned to elevate the issue on the policy agenda. Delphi findings further confirmed consensus regarding the urgency of financing reform and the need for policy action.
Nevertheless, the effective exploitation of this policy window has been constrained by relatively weak policy entrepreneurship. According to Kingdon's theory, policy windows are often short-lived and may close without actors capable of coupling the three streams, mobilizing coalitions, and linking recognized problems with viable policy solutions (11, 13, 18).
Overall, this study reinforces the view that sustainable financing of medical education requires simultaneous attention to economic realities, political feasibility, and institutional capacity. The integration of Walt and Gilson's Policy Triangle with Kingdon's Multiple Streams Framework provides a deeper understanding of how financing challenges reached the policy agenda and why implementation of financing reforms remains difficult despite increasing policy attention.
Conclusion
This study highlights that sustainable medical education financing in Iran, and similarly in many resource-constrained settings, is fundamentally a political and institutional challenge rather than a purely technical or budgetary one. Persistent macroeconomic pressures, including high inflation, international sanctions, and the critically low share of education in GDP and health expenditure, have converged with demographic shifts, technological demands, and ideological commitments to create an increasingly unsustainable situation.
Using Kingdon's Multiple Streams Framework, the findings demonstrate that the problem, political, and policy streams have gradually aligned, opening a rare policy window for meaningful reform. However, the effective exploitation of this window requires stronger policy entrepreneurship and greater institutional coherence than currently exists.
The results underscore the need to move beyond exclusive reliance on traditional public funding toward diversified, transparent, and sustainable financing models that actively engage the private sector while preserving equity and social accountability. Strategic integration of technological innovations should be pursued within robust ethical and regulatory frameworks to improve efficiency without compromising quality.
Ultimately, achieving sustainable financing for medical education depends less on the choice of specific financial instruments and more on the quality of policy processes, governance capacity, and the ability of health systems to reconcile competing economic, political, and social priorities. Although grounded in the Iranian context, the mechanisms identified in this study offer valuable transferable insights for other low- and middle-income countries facing analogous structural and political challenges.
Policy Recommendations
The findings suggest that achieving financing sustainability in medical education requires a gradual transition from reliance on traditional public funding toward more diversified financing arrangements. Policymakers should strengthen performance-based allocation mechanisms, encourage responsible private-sector engagement, improve financial transparency, and align financing strategies with long-term health workforce needs. Greater coordination between health, education, and finance sectors may also facilitate more sustainable resource mobilization and allocation.
Recommendations for Future Research
Future studies should examine sustainable medical education financing in different institutional and national contexts to assess the transferability of the present findings. Comparative policy analyses, longitudinal investigations of financing reforms, and quantitative assessments of financing sustainability indicators may provide additional insights into the effectiveness of alternative financing arrangements.
Strengths and limitations of the study
This study has several strengths. It applies a theory-driven approach by integrating Kingdon's Multiple Streams Framework and Walt and Gilson's Policy Triangle, enabling a comprehensive analysis of agenda-setting dynamics. The mixed-methods design -combining literature review, qualitative interviews, and a Delphi process- enhances robustness through methodological triangulation. Inclusion of stakeholders from different professional backgrounds and a high-response, multi-round Delphi process with strong consensus further strengthen the credibility of the findings. Methodological rigor was ensured through established qualitative techniques and transparent, human-verified use of AI-assisted tools.
However, several limitations should be noted. The study is context-specific to Iran, which may limit the transferability of the findings to other settings. The relatively small sample size and the absence of some stakeholder groups may have restricted the breadth of perspectives captured. In particular, policymakers constituted a smaller proportion of participants than academic stakeholders, which may have limited the representation of political and fiscal governance perspectives related to agenda-setting and financing reforms. Additionally, the study did not include representatives from key financial institutions, such as national budgetary, treasury, or health insurance organizations. Using the same participants in both the interview and Delphi phases may also have introduced bias although this approach facilitated continuity and informed consensus-building. Finally, as with all qualitative research, the findings remain subject to interpretive limitations despite efforts to ensure methodological rigor.
Acknowledgment
The authors gratefully acknowledge the financial support provided by the National Agency for Strategic Research in Medical Education (NASR), Iran, for the research, authorship, and publication of this article. The funding body had no role in the study design, data collection, analysis, interpretation of data, or in the preparation of the manuscript.
Authors' Contribution
All authors contributed to the discussion, reviewed and approved the manuscript, and agreed to be accountable for all aspects of the work, ensuring that any questions related to the accuracy or integrity of any part of the study are appropriately investigated and resolved.
Conflict of Interest
The authors declare no conflicts of interest.
Declaration of AI
AI-assisted tools were also used as supportive instruments for figure design and analytical assistance.
References
- Huang F. Higher education financing in Japan: trends and challenges. Int J Educ Dev. 2017; 55:1-10.
- Yang L, McCall B. World education finance policies and higher education access: a statistical analysis of World Development Indicators for 86 countries. Int J Educ Dev. 2014; 35:25-36.
- He K, Whang E, Kristo G. Graduate medical education funding mechanisms, challenges, and solutions: a narrative review. Am J Surg. 2021; 221(1):65-71.
- Schuster BL. Funding of graduate medical education in a market-based healthcare system. Am J Med Sci. 2017; 353(2):119-25.
- Kim B, Park N. Lessons learned from financing universal higher education in Korea. Int J Educ Dev. 2018; 58:116-27.
- Teichler U. Recent changes of financing higher education in Germany and their intended and unintended consequences. Int J Educ Dev. 2016; 46:1-10.
- Marginson S. Global trends in higher education finance. Int J Educ Dev. 2017; 55:1-8.
- Poz MRD, Couto F, Franco A. Financing challenges in medical education: transition from elite to mass systems. Educ Health (Abingdon). 2016; 29(1):1-8.
- Lung M, Moldovan I, Nistor L, Lung A. Financing higher education in Europe: issues and challenges. Procedia Soc Behav Sci. 2012; 51:938-42.
- Goksu AG, Goksu GG. A comparative analysis of higher education financing in different countries. Procedia Econ Finance. 2015; 26:1152-8.
- Walt G, Gilson L. Reforming the health sector in developing countries: the central role of policy analysis. Health Policy Plan. 1994; 9(4):353-70.
- Chapman B, Doan P. Introduction to higher education financing: student loans. Econ Educ Rev. 2019; 70:1-10.
- Jacob WJ, Neubauer D, Ye L. Global trends in higher education financing. Int J Educ Dev. 2018; 58:1-4.
- Aizenberg DJ, Logio LS. The graduate medical education (GME) gold rush: GME slots and funding as a financial asset. Acad Med. 2020; 95(4):503-5.
- Richards JR, Scheckel C, Newman JR. PROSPER or not? Potential medical education financing reforms and impacts. J Am Osteopath Assoc. 2019; 119(2):72-4.
- Gottlieb M, Lee S, Burkhardt J, Carlson JN, King AM, Wong AH. Show me the money: successfully obtaining grant funding in medical education. West J Emerg Med. 2019; 20(1):71-7.
- Otero HJ, Ondategui-Parra S, Erturk SM, Ros PR. Financing radiology graduate medical education: today's challenges. J Am Coll Radiol. 2006; 3(3):207-12.
- Gury Z. Innovative higher education learning outcomes and financing trends in Israel. Int J Educ Dev. 2018; 58:128-36.
- Bentz ML, Ahmad J, Rohrich RJ. Fundraising and philanthropy in plastic surgery: an essential tool for academic excellence. Plast Reconstr Surg. 2011; 127(5):2108-12.
- Namazi M, Zare S. Calculation of the Cost of Student Education: A Case Study of Shiraz Medical School. J Adv Med Educ Prof. 2021; 9(2):109-22.
- Karimi E, Sohrabi Z, Aalaa M. Change Management in Medical Contexts, especially in Medical Education: A Systematized Review. J Adv Med Educ Prof. 2022; 10(4):219-27.
- Alizadeh M, Jafar Sameri M. Intelligent Assessment Systems in Medical Education: A Systematic Review. J Adv Med Educ Prof. 2025; 13(3):173-90.
- Hwang R, Paley M, Bull D, Omrani O, Vergara-Jalandoni D, Egbury G. A Systematic Review and Meta-Analysis on the Impact of Peer-Made MCQ Question Bank Usage on Summative Assessments in Medical Education. J Adv Med Educ Prof. 2025; 13(4):259-69.
- Toofaninejad E, Rezapour SM, Kalantarion M. Utilizing Digital Twins for the Transformation of Medical Education. J Adv Med Educ Prof. 2024; 12(2):132-3.
- Varpahovskis E. Transnational higher education—the case of Kazakhstan. In: Varpahovskis E. Transnational higher education in the Asia region. SpringerBriefs in political science. Cham: Springer; 2023.
- Burns KH, Borowitz MJ, Carroll KC, Gocke CD, Hooper JE, Amukele T. The evolution of earned, transparent, and quantifiable faculty salary compensation: the Johns Hopkins pathology experience. Acad Pathol. 2018; 5:2374289518777463.
- Richards JR, Scheckel C, Newman JR. PROSPER or Not? Potential Medical Education Financing Reforms and Impacts. J Am Osteopath Assoc. 2019; 119(2):72-4.
- Grewal K, Sweeney MJ. An innovative approach to educating medical students about personal finance. Cureus. 2021; 13(6):e15579.
- Li W, Liu Q. Chinese higher education finance: changes over time and perspectives to the future. Procedia Soc Behav Sci. 2013; 77:388-411.


